HPB stands for hepato-pancreato-biliary: the liver, pancreas, gallbladder and bile ducts.
These organs are closely connected anatomically and functionally. A tumour arising in one may involve another. A pancreatic tumour can obstruct the bile duct. Gallbladder cancer can extend into the liver. A bile duct tumour may require removal of part of the liver. A liver tumour may lie immediately beside major blood vessels that need to be preserved or reconstructed.
This is why complex HPB surgery is not simply about removing an abnormal organ or tumour. It requires an understanding of cancer biology, vascular anatomy, liver function, reconstruction and the full range of surgical and non-surgical treatment options available.
In Dr. Manikandan Kathirvel’s practice, some of the most important referrals are patients who have already been told that their tumour is “inoperable,” patients with persistent biliary obstruction despite repeated procedures, patients with extensive liver tumours or metastases, and patients in whom gallbladder cancer has unexpectedly been discovered after a routine cholecystectomy.
Sometimes the original treatment plan remains the right one. In other patients, specialist HPB review can identify additional options.
The important question is therefore not simply “can this tumour be removed?” It is“what is the best treatment strategy for this patient, and is there a safe way of achieving complete disease clearance while preserving enough normal organ function?”
Key Takeaways
- HPB surgery is the specialist surgical field dealing with complex diseases of the liver, pancreas, gallbladder and bile ducts.
- The relationship of a tumour to major blood vessels can be as important as its size when determining whether surgery is possible.
- Some pancreatic and liver tumours initially considered unresectable may become surgical candidates after systemic treatment, vascular reconstruction or specialised liver surgery strategies.
- Persistent bile duct obstruction needs a diagnosis and a definitive treatment plan rather than repeated treatment of the obstruction alone.
- Gallbladder cancer discovered unexpectedly after cholecystectomy requires prompt specialist staging and HPB review; some patients will require a second, more extensive operation.
- Modern HPB surgery increasingly includes robotic and minimally invasive surgery, vascular reconstruction, parenchymal-sparing liver surgery and transplantation.
- The right approach may be robotic, laparoscopic or open. The disease and the patient should determine the operation, not simply the technology available.
- A second opinion is worth seeking whenever a tumour has been labelled inoperable, a decision involves vascular reconstruction, or there is uncertainty between resection and transplantation, since these are exactly the situations where specialist HPB review most often changes the plan.
What Is HPB Surgery?
General surgery covers a broad range of abdominal conditions. HPB surgery represents further subspecialist training and experience focused on complex diseases of the liver, pancreas, gallbladder and bile ducts.
The distinction becomes particularly important when an operation involves:
- major blood vessels such as the portal vein, hepatic artery, hepatic veins or vena cava
- complex pancreatic or biliary reconstruction
- major or technically difficult liver resection
- vascular resection and reconstruction
- advanced cancer surgery
- assessment of how much functioning liver can safely be removed
- decisions between liver resection and transplantation
- complex minimally invasive or robotic surgery
Modern HPB treatment is also highly multidisciplinary. Depending on the disease, treatment may involve specialist radiologists, gastroenterologists, hepatologists, medical and radiation oncologists, interventional radiologists, transplant physicians and surgeons, pathologists and critical-care teams.
This multidisciplinary approach is particularly important because the first treatment is not always surgery.
When Specialist HPB Review Can Change the Treatment Plan
One of the common patterns seen in practice is a patient arriving with a diagnosis already attached to the case: “inoperable pancreatic cancer,” “too many tumours in the liver,” “nothing more can be done surgically,” “the bile duct keeps blocking, so another stent is required,” or “the gallbladder has already been removed, but the pathology has unexpectedly shown cancer.”
These situations do not necessarily mean that the previous assessment was wrong. Complex cancer treatment evolves, and different patients require different combinations of treatment.
What specialist HPB assessment can add is a detailed review of resectability and the full range of available treatment strategies. Modern HPB surgery may include vascular resection and reconstruction, parenchymal-sparing liver surgery, portal vein embolisation, staged liver resections, systemic treatment followed by reassessment, robotic or laparoscopic surgery and, in selected liver diseases, transplantation.
Some patients will still be best treated without surgery. But particularly in complex disease, a decision that a tumour is “inoperable” should ideally follow review of the imaging and treatment options by an experienced multidisciplinary HPB team.
Pancreatic Tumours
Not every pancreatic tumour is cancer, and not every pancreatic cancer is immediately suitable for surgery.
When pancreatic cancer is diagnosed, one of the first questions is whether the tumour can be completely and safely removed. Tumour size is only part of that assessment. The relationship between the tumour and the surrounding major vessels, particularly the superior mesenteric artery, coeliac axis, hepatic artery, superior mesenteric vein and portal vein, is extremely important. High-quality pancreas-protocol CT imaging is therefore central to planning treatment.
Pancreatic cancers are broadly considered resectable, borderline resectable or locally advanced, following criteria used by major cancer centres and the National Comprehensive Cancer Network, although the final assessment depends on detailed anatomical and clinical factors.
Resectable pancreatic cancer. The relationship between the tumour and surrounding vessels suggests that complete removal is technically achievable. For suitable patients, surgery forms an important part of potentially curative treatment.
Borderline resectable pancreatic cancer. The tumour has a closer or more complex relationship with important arteries or veins, but complete removal may still be possible. These patients commonly receive treatment before surgery, followed by repeat imaging and reassessment. In selected patients, surgery may also require removal and reconstruction of part of the portal vein or superior mesenteric vein.
Locally advanced pancreatic cancer. The tumour has more extensive involvement of surrounding vascular structures and complete surgical removal may not be appropriate at presentation. Systemic treatment is usually the initial strategy. However, the original label of “unresectable” does not always have to be permanent. Selected patients who respond particularly well to treatment may deserve reassessment by an experienced pancreatic multidisciplinary team. This is one of the situations where a specialist second opinion can be valuable.
Surgery for Pancreatic Tumours
The operation depends largely on where the tumour is located.
A tumour in the head of the pancreas may require a pancreaticoduodenectomy, commonly known as the Whipple procedure. This involves removal of the pancreatic head, duodenum, distal bile duct and gallbladder, followed by reconstruction to restore pancreatic, biliary and gastrointestinal drainage.
Tumours in the body or tail of the pancreas may require a distal pancreatectomy, sometimes together with removal of the spleen. Selected pancreatic lesions may be suitable for more limited or organ-preserving procedures.
Increasingly, some pancreatic operations can also be performed using laparoscopic or robotic approaches in appropriately selected patients. The important principle is that minimally invasive surgery should never compromise cancer clearance, lymph-node dissection, vascular control or the quality of reconstruction.
For how robotic technique applies to the Whipple procedure and what recovery involves, see Robotic Liver and HPB Surgery: Where It Adds Value and When It Is Recommended.
Bile Duct Obstruction
The bile ducts carry bile produced by the liver into the intestine. When this pathway becomes blocked, patients may develop jaundice, dark urine, pale stools, itching, abdominal pain, fever or cholangitis, and abnormal liver blood tests.
The important question is not simply how to relieve the obstruction, but why the bile duct is blocked. There are several very different causes.
Gallstones. Stones in the common bile duct are common and can frequently be treated endoscopically, followed by gallbladder surgery when appropriate. Most uncomplicated gallstone disease does not require specialist HPB surgery.
Benign bile duct strictures. Bile ducts may narrow following previous surgery, inflammation or recurrent infection. Some can be treated successfully with endoscopic or radiological intervention. Others, particularly recurrent or complex strictures, may require surgical biliary reconstruction.
Cholangiocarcinoma. Cholangiocarcinoma is cancer arising from the bile duct. Its treatment depends heavily on where along the biliary tree the tumour arises. A perihilar cholangiocarcinoma, arising where the right and left hepatic ducts meet, can be particularly challenging because of its intimate relationship with the liver’s blood vessels and bile ducts. Curative surgery may require not only removal of the affected bile duct but also major liver resection, lymph-node dissection and occasionally vascular reconstruction.
Pancreatic and periampullary tumours. A tumour in the head of the pancreas or around the ampulla can compress or obstruct the lower bile duct, producing jaundice even though the primary disease is not arising from the bile duct itself. This distinction matters because the definitive treatment is completely different.
For the full guide to causes, warning signs and surgical options for bile duct obstruction, see Bile Duct Obstruction: Causes, Warning Signs and Surgical Options.
A Stent Treats the Obstruction, Not Necessarily the Disease
Endoscopic or radiological stenting can be extremely valuable. It can relieve jaundice, treat or prevent cholangitis and allow patients to proceed safely to further treatment.
But repeated biliary stenting does not replace establishing the underlying diagnosis and determining whether definitive treatment is possible. Persistent, recurrent or unexplained biliary obstruction therefore deserves specialist assessment, particularly when malignancy remains a possibility.
Liver Tumours and Complex Liver Resection
Liver tumours broadly include primary liver cancers, tumours that have spread to the liver from elsewhere, and selected benign or indeterminate lesions. The surgical principles are different for each.
Hepatocellular Carcinoma
Hepatocellular carcinoma (HCC) most commonly develops in a liver affected by chronic liver disease or cirrhosis. This creates an unusual surgical problem: the surgeon is treating both a tumour and an abnormal liver.
For some patients, liver resection is appropriate. For others, liver transplantation may offer an advantage because transplantation treats both the cancer and the underlying diseased liver. The decision depends on several factors, including:
- tumour number and size
- tumour location
- liver function
- presence and degree of portal hypertension
- the amount and quality of liver that would remain after resection
- suitability for transplantation
This is one area where having both HPB and transplant expertise within the treating team can be particularly valuable. The question is not simply whether the tumour can technically be removed. It is whether resection or transplantation offers the more appropriate long-term strategy for that individual patient.
For the full clinical breakdown of HCC, resection-versus-transplant decision-making, and survival data, see Liver Transplant in Chennai: The Complete Patient Guide.
The Future Liver Remnant: A Central Principle in Liver Surgery
One of the most important concepts discussed with patients undergoing major liver surgery is the future liver remnant.
The liver has an extraordinary ability to regenerate, but a patient still needs enough functioning liver immediately after surgery to recover safely. Therefore, before a major liver resection, the central question is: can all of the tumour be removed while leaving enough healthy, functioning liver behind?
This calculation depends not only on the amount of liver remaining but also on its quality. A healthy liver, a fatty liver, a chemotherapy-treated liver and a cirrhotic liver do not have the same functional reserve.
When the predicted remaining liver is inadequate, specialised strategies such as portal vein embolisation can sometimes be used before surgery to encourage the future liver remnant to grow. In selected patients, this can make major liver surgery safer and can sometimes make an operation possible that would otherwise carry an unacceptable risk of postoperative liver failure.
Colorectal Liver Metastases
Cancer arising in the colon or rectum commonly spreads to the liver. This does not automatically mean surgery is impossible.
For appropriately selected patients, removal of colorectal liver metastases can provide meaningful long-term survival and, in some patients, the possibility of cure. Modern treatment has substantially expanded the range of patients who can be considered for surgery. Strategies can include:
- systemic treatment followed by reassessment
- parenchymal-sparing liver resections
- multiple liver resections during the same operation
- staged liver surgery
- portal vein embolisation
- combinations of surgery and other tumour-directed treatments
This is why the number of tumours alone does not determine operability. The more important question is whether all relevant diseases can be treated while preserving an adequate amount of functioning liver. A patient with liver metastases who has been told that surgery is not possible may therefore reasonably seek a specialist HPB opinion before accepting that conclusion as final.
Gallbladder Cancer
Gallbladder cancer is particularly important because it is sometimes discovered unexpectedly. A patient may undergo what appears to be a routine cholecystectomy for gallstones or gallbladder inflammation, recover from surgery, and then receive an unexpected pathology report showing cancer. This is known as incidental gallbladder cancer. What happens next can be extremely important.
If Cancer Is Found After Gallbladder Surgery, What Should Happen Next?
When a patient is seen after an unexpected diagnosis of gallbladder cancer following cholecystectomy, the first message given to the family is direct: there is no need to panic, but specialist assessment should not be delayed.
The next step is not automatically another operation. What is needed first is a clear understanding of exactly what was found. This usually involves:
- careful review of the histopathology
- determining the depth and stage of the tumour
- reviewing the cystic duct and other relevant margins
- understanding whether the gallbladder was perforated or whether there was bile spillage during the original operation
- reviewing the original operative findings
- appropriate staging imaging to look for residual or metastatic disease
Only after this assessment should the need for further surgery be decided.
Does Every Incidental Gallbladder Cancer Need Another Operation?
No. A T1a gallbladder cancer, confined to the lamina propria, is generally adequately treated by the original cholecystectomy if it has been completely removed; reported five-year survival for this group approaches 100%.
For disease extending beyond this earliest stage, particularly T1b and T2 tumours, specialist HPB assessment is required to determine whether complete radical surgery is appropriate. Depending on the stage and findings from the original operation, this may include removal of liver tissue adjacent to the gallbladder bed together with regional lymph-node dissection. More extensive liver, bile duct or adjacent-organ resection is reserved for selected situations where it is necessary to achieve complete cancer clearance. Surgical series report five-year disease-free survival above 50% in patients who go on to complete appropriate resection.
The objective is not to perform the largest operation possible. It is to perform the operation necessary to achieve appropriate cancer clearance while avoiding unnecessary additional surgery.
How Urgent Is the Second Operation?
This is one of the most common questions families ask. The urgency lies in obtaining the correct HPB assessment and staging promptly, rather than simply rushing into another operation.
Once the pathology has been reviewed and appropriate staging has excluded disease that would make further surgery inappropriate, completion surgery can be planned within the appropriate oncological timeframe. What should be avoided is a patient with incidental gallbladder cancer being placed into routine follow-up without first establishing whether further treatment is required.
The message to families is simple: an unexpected gallbladder cancer diagnosis after cholecystectomy does not automatically mean another operation, but it does mean that specialist HPB review should not be delayed.
How HPB Surgery Differs From General Surgery
General surgeons are trained to manage a broad range of surgical conditions including appendicitis, hernias, gallstone disease, bowel conditions and emergency abdominal surgery. HPB surgery represents further subspecialist training and experience in complex diseases of the liver, pancreas and biliary system.
The difference becomes particularly relevant in several areas.
Major vascular structures. Complex HPB operations frequently require dissection around the portal vein, hepatic artery, superior mesenteric vessels, hepatic veins and vena cava. In selected cases, these vessels may need to be resected and reconstructed.
Complex reconstruction. A Whipple procedure involves removal of the diseased structures followed by reconstruction of the pancreatic, biliary and gastrointestinal systems. Complex bile duct surgery may similarly require fine biliary reconstruction.
Liver physiology. Liver surgery requires an understanding not only of anatomy but also of how much a functioning liver can safely be removed and how the quality of the remaining liver affects postoperative recovery.
Cancer biology and resectability. Determining whether a pancreatic, liver, gallbladder or bile duct cancer is operable often requires more than deciding whether a tumour can technically be removed. Cancer clearance, vascular involvement, response to systemic treatment and alternative treatment strategies all need to be considered.
Transplantation. For selected liver cancers and chronic liver diseases, the decision may ultimately be between liver resection and transplantation, rather than simply between surgery and no surgery.
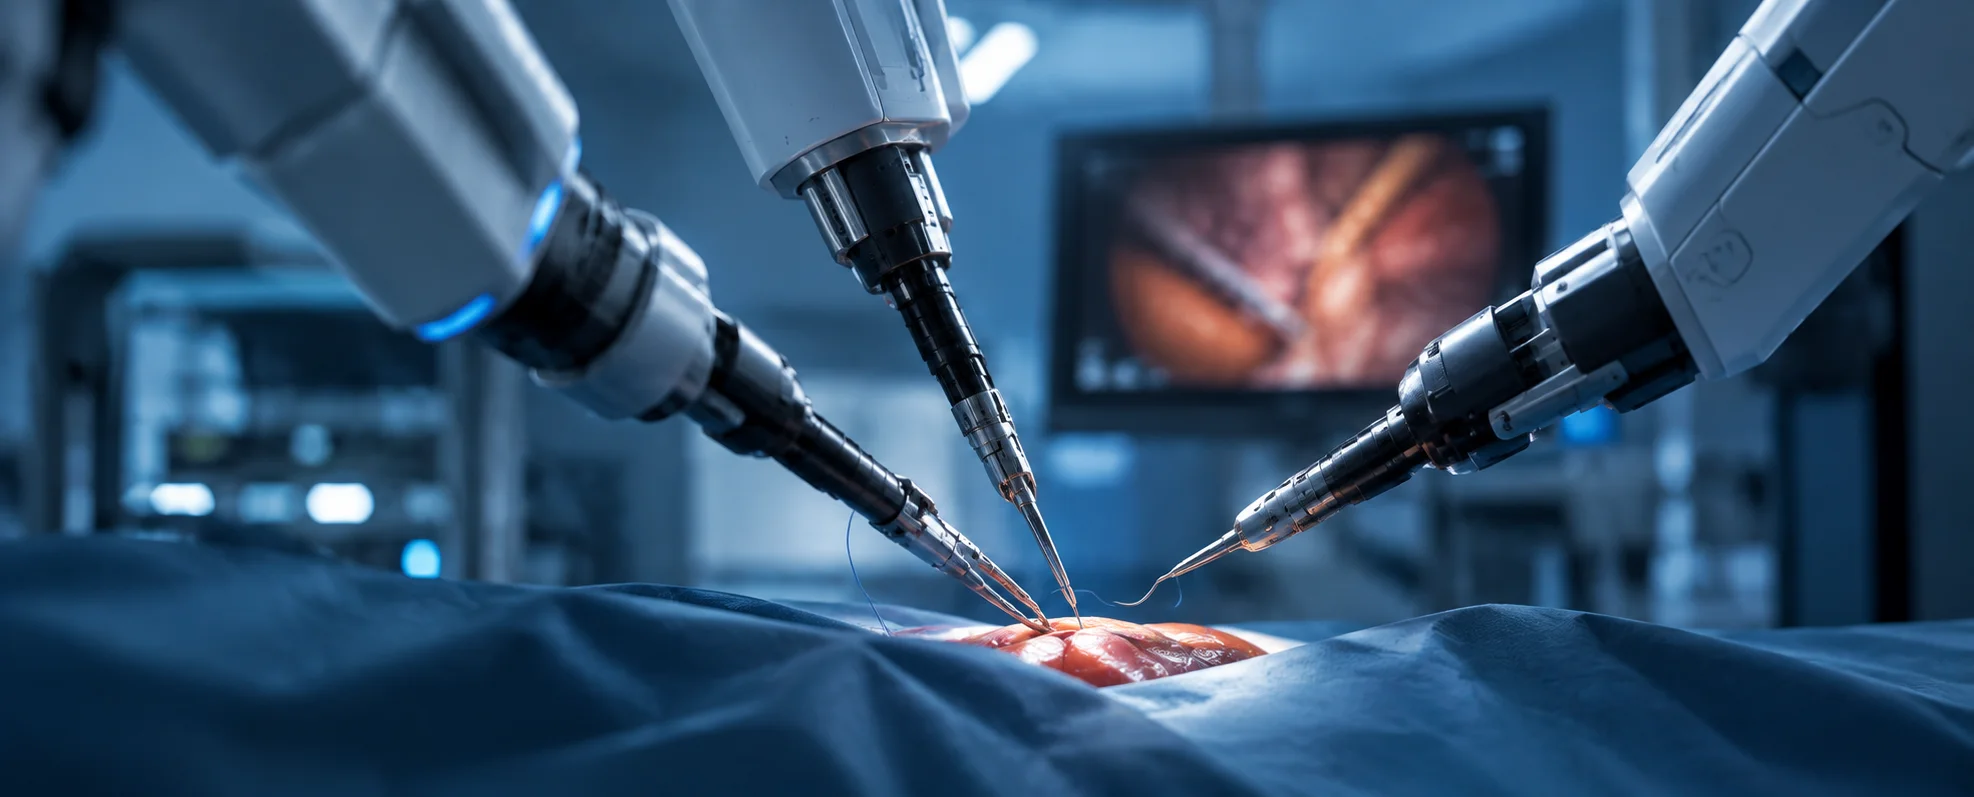
Robotic and Minimally Invasive HPB Surgery
Modern HPB surgery is increasingly performed using minimally invasive techniques. Selected liver resections, distal pancreatic resections, Whipple procedures and complex biliary operations can now be performed using laparoscopic or robotic surgery.
Robotic surgery provides magnified three-dimensional vision and highly articulated instruments, which can be particularly useful during precise vascular and biliary dissection and complex reconstruction. However, not every patient should undergo robotic surgery. The approach should be selected according to the disease, anatomy and operation required.
The question should not simply be “can this be done robotically?” It should be: does a robotic approach offer a meaningful advantage for this patient while maintaining the safety and quality of the operation?
For the full evidence base on robotic liver, pancreatic and biliary surgery, including where it is well established and where it remains emerging, see Robotic Liver and HPB Surgery: Where It Adds Value and When It Is Recommended.
When Should a Patient Consider an HPB Second Opinion?
A second opinion does not necessarily mean that the original treatment plan is wrong. It can be particularly valuable when the decision is complex or when several different treatment strategies may be possible.
An HPB second opinion is worth considering if:
- a pancreatic tumour has been described as borderline resectable or unresectable
- a liver tumour or liver metastases have been described as inoperable
- gallbladder cancer has unexpectedly been found after cholecystectomy
- jaundice or bile duct obstruction keeps recurring despite stenting
- major liver or pancreatic surgery has been recommended
- vascular resection or reconstruction may be required
- there is uncertainty between liver resection and transplantation
- there is a need to understand whether robotic, laparoscopic or open surgery is most appropriate
A good second opinion should not simply offer another operation. It should help clarify the diagnosis, the available treatment options, and why one strategy may be more appropriate for that particular patient.
Getting a Second Opinion
Patients seeking an HPB second opinion can make the consultation more useful by bringing:
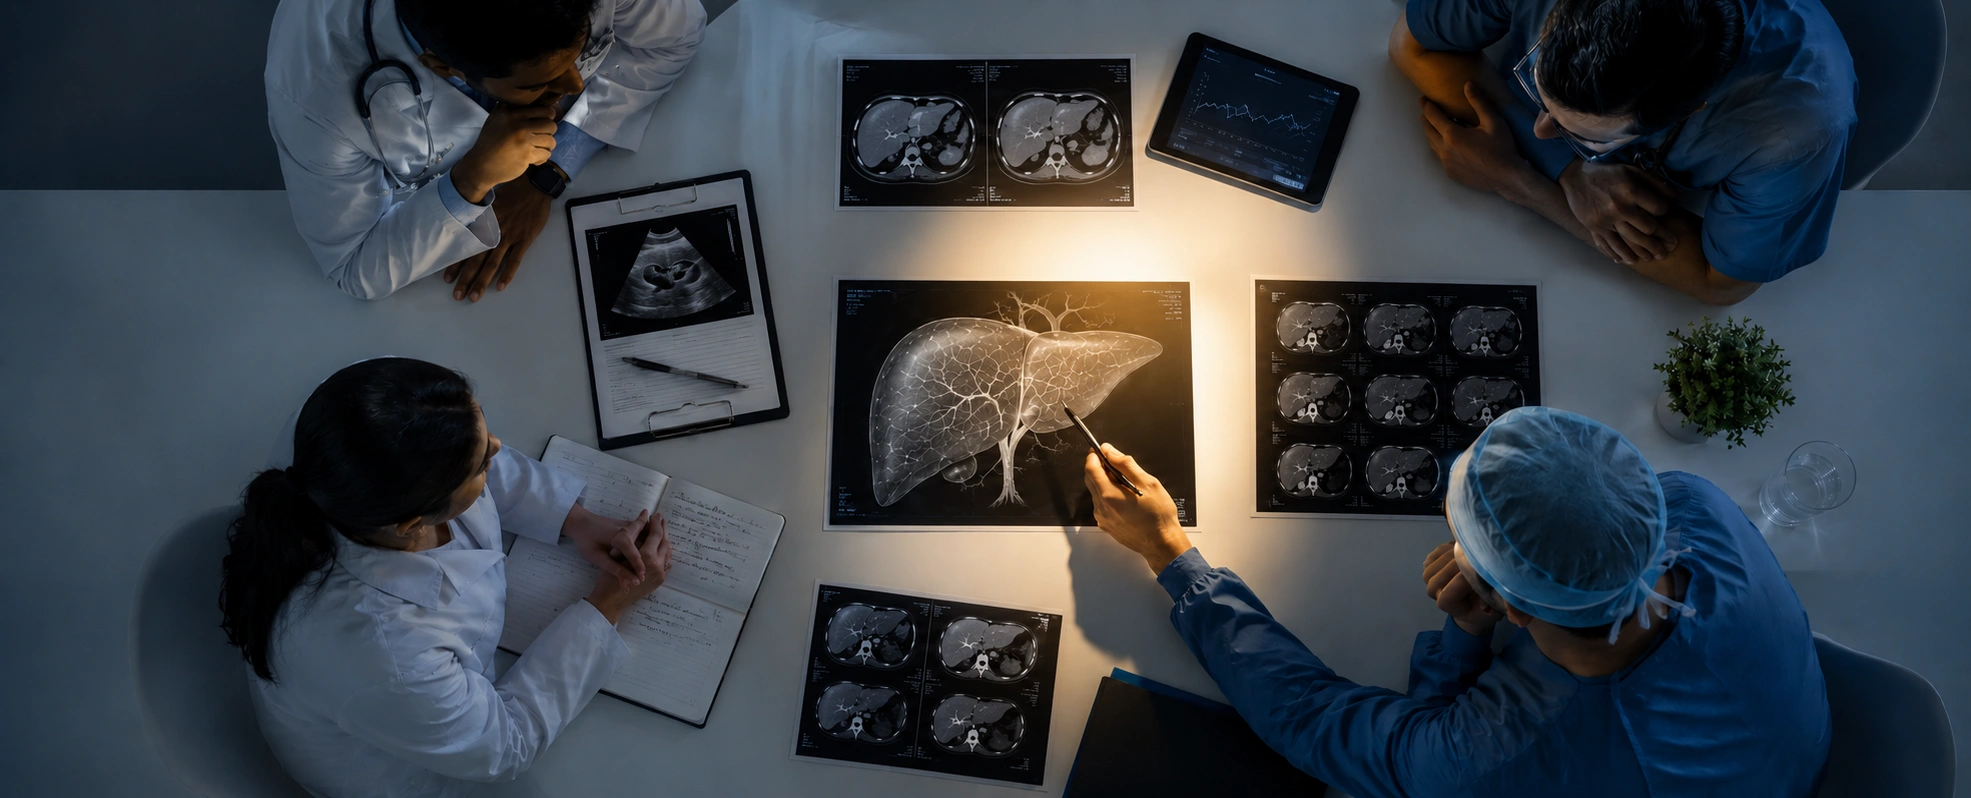
- CT and MRI images, not only the written reports
- PET-CT images where relevant
- histopathology and biopsy reports
- endoscopy, EUS or ERCP reports
- previous operative notes
- chemotherapy or radiotherapy details
- recent blood investigations
- previous discharge summaries
For complex liver and pancreatic disease, reviewing the actual imaging is particularly important because resectability frequently depends on anatomical relationships that cannot always be fully appreciated from a written report alone.
Patients and families can request an HPB surgical evaluation.
About Dr. Manikandan Kathirvel
Dr. Manikandan Kathirvel is a Consultant HPB and Multi Organ Transplant Surgeon at Gleneagles Hospital (Fortis Network), Chennai.
He underwent extensive surgical training in the United Kingdom in complex hepatobiliary, pancreatic and multi-organ transplant surgery, including advanced multi-organ transplant fellowship training at Cambridge University Hospitals, together with HPB and liver transplant experience at the Royal Free London. He holds FRCS in Transplant Surgery from the Royal College of Surgeons of Edinburgh.
His clinical practice encompasses complex liver and pancreatic surgery, liver transplantation, robotic and minimally invasive HPB surgery, vascular reconstruction and the surgical management of complex biliary disease. His combined experience in HPB and transplant surgery allows patients with complex liver disease and liver tumours to be evaluated across a broad spectrum of surgical options, including liver resection, minimally invasive and robotic surgery, vascular reconstruction and transplantation where appropriate.
For his full training history, credentials and academic background, see Liver Transplant in Chennai: The Complete Patient Guide.
Patients and families can request an appointment or second opinion.